What this compound is and where it is present
Propylene glycol is a dissolving agent and delivery agent employed in a range of medical and nonmedical products. In clinical environments, it is most important because it can appear in IV medications, especially certain sedatives and other formulations that need a liquid base. It can also be included in some oral products and topical products. Most exposures are harmless, but large or prolonged exposure can create a toxicity problem, especially in hospitalized patients.
This matters since propylene glycol is not just an ingredient; it is a compound that is metabolized by the body into other substances. Under the right situations, those metabolites can affect acid-base balance and lead to abnormal serum chemistry findings. In some patients, the clinical picture includes high anion gap findings, especially when the exposure is significant or renal clearance is impaired.
From a diagnostic workup standpoint, propylene glycol exposure is often overlooked unless the medication list is reviewed closely. That is why laboratory interpretation must be paired with clinical correlation. The product source, route of NAGMA causes exposure, and duration all influence whether propylene glycol becomes clinically relevant.
How the anion gap is calculated
The anion gap is a derived value used to assist in identifying certain types of metabolic acidosis. It reflects the difference between observed cations and tested anions in the blood. The usual anion gap formula uses serum sodium, serum chloride, and serum bicarbonate.
A streamlined version is:
anion gap = serum sodium − (serum chloride + serum bicarbonate)
An anion gap calculator automates this calculation and can help clinicians and patients see whether the result lands in a normal span or points to an acid-base imbalance. Because the result depends on the measured electrolyte values, even small electrolyte changes can affect the number.
The anion gap is important because unmeasured anions can increase in the blood during conditions such as lactic acidosis, ketoacidosis, or toxin ingestion. When interpreting the number, clinicians also consider albumin, since low albumin can decrease the measured gap and obscure a clinically important issue. That is why the albumin-corrected anion gap is often more informative than the unadjusted value.
How propylene glycol can increase the anion gap
Yes, propylene glycol can cause a high anion gap in the setting of propylene glycol toxicity. The mechanism is usually not direct rather than sudden. After exposure, propylene glycol is broken down into acidic compounds, including organic acids, which can promote high anion gap metabolic acidosis. In addition, the body may develop a coexisting lactic acidosis, which additionally increases the gap.
Another important clue is the osmolar gap. Propylene glycol itself elevates serum osmolarity, so early toxicity may present with an high osmolar gap before the anion gap rises. As metabolism continues, the parent compound falls while acidic metabolites collect, shifting the pattern from isolated osmolar gap elevation to a combined osmolar gap and high anion gap pattern.
This progression is why the moment of testing matters. A patient may initially have a high osmolar gap and later show increasing acidosis, elevated lactate, and a rising anion https://anion-gap-widget015.bearsfanteamshop.com/how-the-anion-gap-aids-identify-acid-base-disorders gap. In other words, propylene glycol can be part of a combined laboratory pattern that develops over time.
Common causes of high anion gap metabolic acidosis
Propylene glycol is only one possible cause of metabolic acidosis. A comprehensive differential diagnosis is necessary whenever the anion gap is elevated. Common causes include ketoacidosis, lactic acidosis, renal failure, and use of toxic alcohols. Any of these can cause a similar lab pattern, but the underlying mechanism is different.
Ketoacidosis is often seen with diabetes, starvation, or prolonged vomiting, while lactic acidosis may occur with shock, sepsis, hypoperfusion, or certain drugs and toxins. Renal failure can raise the gap because the kidneys cannot clear acid effectively, allowing unmeasured acids to accumulate. Toxic alcohols, such as methanol or ethylene glycol, can also produce an elevated anion gap and osmolar gap pattern.
This is why laboratory interpretation should never rely on a single number alone. The anion gap calculator can identify a concerning result, but the final diagnosis depends on the clinical context, medication exposure, and additional testing.
Symptoms and manifestations of propylene glycol toxicity
The manifestations of propylene glycol toxicity can be unclear at first. Patients may present with altered mental status, hypotension, and tachypnea as the acid-base imbalance worsens. Tachypnea often reflects respiratory compensation for acidosis. Some patients may also show signs of worsening perfusion or sedation, depending on the degree of exposure and the agents used.
A rising serum lactate can be an key clue, especially when the clinical picture suggests an unexplained acid-base disorder. Elevated lactate does not prove propylene glycol as the cause, but it strengthens concern when combined with medication exposure, abnormal serum chemistry, and a high anion gap. Because the symptoms overlap with other illnesses, clinical correlation is important.
Severe cases can progress quickly, particularly when the patient has poor elimination or multiple risk factors. A careful review of medications, infusion history, and serial labs is often the fastest way to recognize the problem.
Tests used to evaluate suspected toxicity
When propylene glycol exposure is suspected, the evaluation usually includes serum osmolality, assessment of the osmolar gap, a blood gas, and checking of renal function. These studies help determine whether the patient has a mixed toxic and metabolic picture.
Serum osmolality is compared with the calculated osmolarity to identify an osmolar gap. An elevated gap suggests unmeasured osmotically active substances, which may include propylene glycol or other toxic alcohols. The blood gas helps define the severity of the acid-base disorder and shows whether the patient has metabolic acidosis with respiratory compensation. Renal function testing is important because reduced clearance can worsen toxicity and prolong exposure.
Other lab studies often include serum lactate, electrolytes, and repeat chemistry panels. Serial testing can show whether the anion gap is rising or resolving after intervention. In many patients, the pattern of serum chemistry abnormalities provides the strongest evidence before specialized toxin levels are available.
How to understand an Anion Gap Calculator output
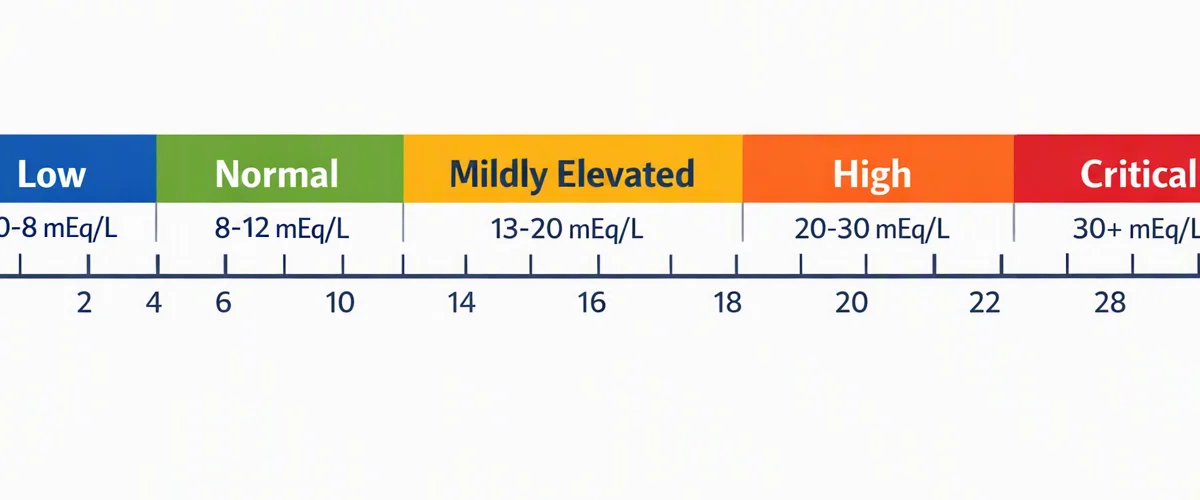
An anion gap calculator is valuable, but the finding should consistently be interpreted in context. First, check whether the value is in the normal range for the facility used. Normal ranges can differ a bit depending on the analyzer and whether potassium is included in the formula. A value that is borderline in one lab may be clearly abnormal in another.
Afterward, evaluate the possibility of hypoalbuminemia. Since albumin is a major unmeasured anion, low albumin can mask a true acidosis. An albumin-corrected anion gap gives a better estimate of the underlying acid burden when albumin is reduced. This adjustment is particularly helpful in critically ill patients, where albumin is often low.
Finally, ask whether the result matches the overall picture. A high anion gap with normal lactate and normal ketones may indicate a toxin, while a high gap with elevated lactate may point to tissue hypoperfusion, sepsis, or propylene glycol toxicity. Good interpretation depends on clinical context, not just the number.
When exposure to propylene glycol becomes dangerous
Danger grows with dose-related toxicity, longer exposure, and limited ability to eliminate the compound. This is especially relevant with some benzodiazepines and other intravenous medications that include propylene glycol as a solvent. Continuous, high-dose infusion can result in accumulation over time.
Renal impairment increases risk because the kidneys have a key role in eliminating the compound and its byproducts. If renal clearance is reduced, propylene glycol and its metabolites may collect, pushing the patient toward osmolar gap elevation, lactic acidosis, and high anion gap metabolic acidosis.
Risk peaks when multiple factors combine: high medication dose, prolonged infusion, critical illness, dehydration, and impaired kidney function. In that setting, monitoring should be closer and clinicians should stay highly alert for toxicity.
Treatment and management of suspected propylene glycol toxicity
The first step in management is discontinuation of the suspected source. Stopping the offending medication or exposure can avoid more accumulation. Depending on the severity of the case, the patient may also need supportive care, including fluid resuscitation, correction of electrolyte abnormalities, and treatment of acidosis.
Monitoring is important after the exposure is stopped. Serial serum chemistry testing, blood gas assessment, serum lactate, and renal function checks help show whether the acid-base disorder is improving. If the patient has severe symptoms, rapidly worsening acidosis, or significant renal dysfunction, more aggressive treatment may be needed.
Hemodialysis can be considered in severe cases because it helps remove propylene glycol and correct associated metabolic derangements. It may be especially useful when there is significant acidosis, hemodynamic instability, or impaired renal clearance. The decision is based on the full clinical picture rather than the anion gap alone.
When to require immediate medical evaluation
Prompt evaluation is needed if there are critical warning signs such as increasing confusion, marked weakness, breathing difficulty, collapse, or shock symptoms. A patient with suspected toxic exposure and a suddenly worsening condition should not wait for routine follow-up.
Concerning features include severe acidosis, markedly low bicarbonate, persistent hypotension, or fast-rising lactate. These findings may signal a serious acid-base disorder that needs urgent treatment. If propylene glycol exposure is possible, a timely medical assessment can identify whether the patient needs hospital monitoring, medication changes, or hemodialysis.
Because the condition can overlap with other causes of high anion gap metabolic acidosis, clinicians should evaluate the entire presentation early. Prompt review of medication exposure, serum osmolality, blood gas results, and renal function can prevent delays in care.
Frequently asked questions about propylene glycol and the anion gap
Can propylene glycol cause a high anion gap?
It can. Propylene glycol can cause a high anion gap, especially when exposure is significant or prolonged. It may first raise the osmolar gap and then, as it is metabolized into acidic metabolites, contribute to high anion gap metabolic acidosis and lactic acidosis.
What is the difference between an anion gap and an osmolar gap?
The anion gap shows unmeasured charged particles and helps detect causes of metabolic acidosis. The osmolar gap reflects the difference between measured and calculated osmolarity and suggests unmeasured dissolved substances, such as propylene glycol or other toxic alcohols. Both are important, but they serve different questions.
Which medications contain propylene glycol?
Propylene glycol can be found in some intravenous medications, including certain benzodiazepines, sedatives, and other formulations that use it as a solvent. It may also appear in some oral products and topical products. The exact formulation depends on the drug and manufacturer, so the medication list should be checked carefully.
What indications suggest propylene glycol toxicity?
Possible signs include changes in consciousness, hypotension, increased respiratory rate, and evidence of worsening acidosis. A rising serum lactate may also be present. Since these findings are non-specific, they must be assessed with exposure history, lab values, and total clinical correlation.
How is propylene glycol toxicity treated?
Management usually starts with discontinuation of the source and supportive care. Clinicians follow the patient closely with repeat labs, including blood gas, serum chemistry, and renal function. In severe cases, hemodialysis may be used to help remove the toxin and correct severe acidosis.