What Is the Anion Gap?
The anion gap is a calculated value that helps estimate the balance between measured positively charged and negatively charged electrolytes in the blood. It is commonly used as a preliminary test in acid-base balance because it can suggest hidden problems that may not be obvious from a basic lab result alone. The Anion Gap Calculator uses a set of common measurements from a blood test to generate this value efficiently and reliably.
In plain terms, the calculation compares sodium with chloride and bicarbonate. These are core electrolytes found on many routine panels, including a serum chemistry panel. Because the body must keep these minerals in a limited range, changes in their relationship can suggest an underlying issue.
The anion gap does not measure every ion in the body. Instead, it approximates the difference between the major cations and anions that are directly reported. That is why it is useful as a diagnostic aid rather than a stand-alone diagnosis. It helps inform interpretation, comparison, and medical review when values appear outside the expected pattern.
How the Anion Gap Calculator Functions
An Anion Gap Calculator applies a common formula using serum sodium, serum chloride, and serum bicarbonate. The calculation is meant to measure the difference between the listed cations and anions in the electrolyte panel. The result can help identify whether there may be an abnormal accumulation of acids or an unusual electrolyte imbalance.
The standard formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some clinicians use slight variations depending on the lab method or local reporting practices, but this basic version is the best known. The calculator is especially useful because it reduces manual calculation error and gives a rapid, repeatable measurement from a standard serum chemistry panel.
The main inputs are:
- Serum sodium: the main positive electrolyte in the calculation Serum chloride: the main negative electrolyte subtracted from sodium Serum bicarbonate: another essential negative component included in the comparison
By using these values, the calculator produces a number that can be compared with the expected reference range. That comparison supports interpretation of possible metabolic acidosis, compensation patterns, or other abnormalities in the lab result.
Step-by-Step Computing
Using the the calculator one step at a time is simple if you have the blood chemistry values ready at hand. The most important part is providing the correct measurement units and numbers exactly as reported.
Step 1: Locate the serum sodium value on the lab report. This is usually shown in milliequivalents per liter or a similar unit used in chemistry reporting.
Step 2: Locate the serum chloride value. This measurement reflects one of the main anions in the electrolyte panel.
Step 3: Find the serum bicarbonate value, often listed as CO2 or total CO2 on a chemistry panel. This is the bicarbonate number used in the formula.
Step 4: Sum chloride and bicarbonate together. This creates the combined negative side of the calculation.
Step 5: Take away that total from sodium.
Step 6: Review the result with the normal range or reference range used by the lab.
Below is a simple example of the calculation steps:
Sodium 140 − (Chloride 104 + Bicarbonate 24) = 12
In this example, the anion gap is 12, which may be within a normal range depending on the laboratory’s method. The exact interpretation depends on the lab values, the units, and the clinical context. The calculator is best used as a quick calculation tool that helps, but does not replace, medical interpretation.
Standard Anion Gap Ranges and Why They Matter
The normal range for the anion gap can vary from lab to another facility because of discrepancies in measurement methods and equipment. That is why the reference range listed on the report is more important than a single universal number. A value that is normal for one lab may be somewhat different at another.
In general, a normal anion gap suggests that the measured electrolytes are in a balanced pattern. That does not automatically mean everything is normal, but it often means there is no obvious excess of unmeasured acids. A result outside the expected range may need additional review with other lab values and clinical information.
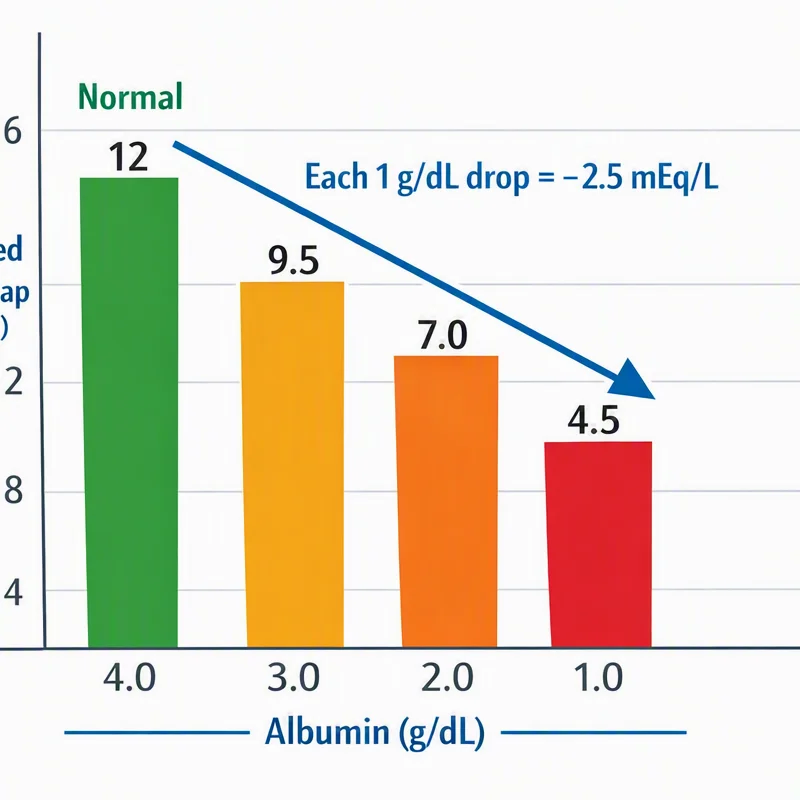
Albumin also matters because it is a major negatively charged protein in the blood. If albumin is low, the anion gap can appear lower than expected even when there is an underlying problem. This is one reason why lab values should be interpreted with consideration of protein status and overall health.
A useful way to think about the number is that it reflects a equilibrium point in the blood’s chemistry. The calculation is not a diagnosis by itself, but it can assist with a broader assessment of acid-base balance and possible causes of an abnormal value.
High Anion Gap Compared with Low Anion Gap
A elevated anion gap often suggests that extra acids are detected in the blood, which can be associated with metabolic acidosis. In this case, the gap is widened because bicarbonate is being used up or replaced by unmeasured acids. This makes the calculation important in practice when evaluating an electrolyte imbalance.
A low anion gap is uncommon, but it can still be significant. It may occur because of low albumin, lab variation, or unusual changes in measured ions. Although less pronounced than a high result, a low gap can still deserve interpretation if it persists or appears with other abnormal findings.
The difference between the two is not just numerical. A high result often points toward acid accumulation, while a low result may indicate a protein-related issue, a measurement problem, or a shift in electrolytes. The final significance depends on the blood test pattern, symptoms, and the rest of the chemistry panel.
Common Causes of an Abnormal Result
Different conditions can lead to an unexpected finding, especially when the value is high. One of the most common causes is lactic acidosis, which happens when lactic acid builds up faster than the body can remove it. This can occur in severe illness, poor oxygen supply, or other physiologic stress states.
Ketoacidosis is also an important cause. In this condition, the body produces ketones as an alternate energy source, and these acids can raise the gap. It is often discussed https://pastelink.net/9srcz4c3 in relation to diabetes, but the core point is that too much acid alters the calculation and suggests metabolic acidosis.
Kidney failure can also raise the anion gap because the kidneys are less able to remove acids efficiently. As acids build up, the gap may rise. This is why the result is often considered alongside other kidney-related lab findings.
Toxins may also change the gap. Certain ingestions or encounters can produce acids or interfere with normal chemistry patterns. In these situations, the anion gap can serve as an early sign that requires prompt medical review.
Not every abnormal value has a dangerous cause, but every abnormal value should be placed in clinical context. The same number can mean something else depending on symptoms, medications, hydration, and related blood test results.
How to Compensate for the Anion Gap for Serum Albumin
Because albumin has a negative charge, a low albumin value can make the anion gap seem artificially low. This is why many clinicians use an albumin correction when interpreting the result. The goal is to approximate what the number would be if albumin were normal.
Reduced albumin, or hypoalbuminemia, can occur with illness, inflammation, poor nutrition, liver problems, or protein loss. When albumin is low, the measured gap may miss the real acid-base disorder. A corrected anion gap can therefore deliver a more precise picture.
The adjustment is usually done with a correction factor based on how far albumin is from the expected level. Different practices may use slightly different approaches, but the principle is the same: take into account the contribution of protein to the acid-base balance.
This correction is especially important when the result appears within range or low but the patient still has signs of metabolic acidosis. In those situations, albumin correction can uncover a hidden abnormality that would otherwise be missed.
Limitations of the Calculator
Although a carefully built calculator has boundaries. One important issue is lab error, which can influence any blood test and alter the final number. A small mistake in one input may lead to a misleading result, so it is always important to checking the source measurements before making conclusions.
Unit conversion is another typical concern. If values are entered in the wrong unit or copied from a report without understanding the reporting format, the result may be incorrect. The calculator depends on precise input and consistent units.
Measurement variability also matters. Different laboratories may use different instruments, methods, or reference intervals, which can affect the reported number slightly. This is one reason why comparison with the lab’s own reference range is more useful than relying on a single universal cutoff.
Most importantly, the result should always be interpreted in clinical context. The calculator is a helpful diagnostic aid, but it cannot judge symptoms, medications, underlying illness, or the full pattern of electrolytes. A number alone cannot make a diagnosis.
When to Request Medical Interpretation
If an abnormal anion gap is found on a blood test, the next step is often a medical evaluation. This is especially true if the result is paired with symptoms or other concerning lab findings. The meaning of the number NAGMA causes depends on the entire clinical picture, not just the calculation itself.
Symptoms such as confusion, severe weakness, shortness of breath, vomiting, dehydration, or sudden worsening illness may indicate that the abnormal value is clinically important. In these cases, prompt review can help determine whether the issue is related to metabolic acidosis, a toxin exposure, kidney failure, or another urgent problem.
Urgent care may be appropriate if symptoms are severe or if the abnormal result appears alongside unstable vital signs or major electrolyte abnormalities. Even when the calculator shows only a mild abnormal value, clinical significance can be high if the person is unwell.
If the result seems borderline or unexpected, the best next step is often a physician review of the full panel, repeat testing when needed, and review of albumin, kidney function, and other associated measurements.
Common Questions
What is the formula for calculating the anion gap?
A common anion gap formula is: anion gap = sodium − (chloride + bicarbonate). This formula uses values from the serum chemistry panel and helps estimate the balance of measured electrolytes. Certain laboratories use slightly different formulas, so it is important to compare the result with the lab’s own method and reference range.
What is a normal anion gap?
Normal values depend on the laboratory’s normal values and reference range. A lot of labs report a range that reflects their specific measurement method. Because of this variation, the clearest interpretation is to look at the range printed on the blood test report rather than using one universal cutoff.
Why would the anion gap be high?
A high anion gap often points to extra acids in the blood, which can happen with lactic acidosis, ketoacidosis, kidney failure, or toxins. It may also point to metabolic acidosis. The result should be interpreted with the rest of the electrolyte panel and the patient’s symptoms to clarify the clinical meaning.
Why might the anion gap be low?
A low anion gap can occur with hypoalbuminemia, lab error, or other changes in measured electrolytes. Since albumin is a key negatively charged protein, low albumin can lower the gap even when the underlying acid-base balance is not truly normal. Measurement variability and clinical context should also be considered.
Is albumin correction needed for the anion gap?
Yes, correcting for albumin is often helpful when albumin is low or when the result does not match the clinical picture. A corrected anion gap can reveal abnormalities that a raw value might miss. This adjustment is very important in hypoalbuminemia because the protein level directly affects the interpretation and the overall acid-base balance.