Understanding the Anion Gap?
The anion gap is a computed value that helps clinicians assess the balance between positively charged and minus-charged particles in the blood. It is derived from common electrolytes on a blood chemistry panel, usually including sodium, chloride, and bicarbonate. Because some ions are not directly measured, the anion gap provides a useful view into overall acid-base balance.
In simple terms, the anion gap helps show whether there may be extra acids in the body or whether something is altering the usual relationship between measured ions. That is why it is often used as a diagnostic clue when reviewing serum chemistry results. The anion gap calculator automates this process, but it still remains useful to understand what the numbers mean before you calculate anion gap values.
The key idea is that the blood contains both cation and anion components. Sodium is the main measured cation, while chloride and bicarbonate are the main measured anions in the formula. The gap shows the difference between these measured values and the unmeasured substances in the blood, often referred to as unmeasured anions.
When Is It Appropriate to Use an Anion Gap Calculator?
You should apply an anion gap calculator when checking an electrolyte panel and you want to review possible metabolic acidosis or a different acid-base disorder. It is especially valuable when the clinical interpretation of lab values is not obvious from the individual numbers alone. A calculator can quickly distill the pattern and improve more accurate result interpretation.
This tool is frequently used when a patient has symptoms or lab findings suggesting a metabolic imbalance, such as low bicarbonate, abnormal chloride, or other changes in the electrolyte values. It can also help interpret a blood chemistry panel when the lab reference values point toward an acid-related problem.
Common situations where it helps include:
- Possible metabolic acidosis Unexplained changes in the electrolyte panel Low bicarbonate with uncertain cause Worry for toxin exposure or other causes of acid accumulation Monitoring a known acid-base disorder
The calculator does not stand in for a full clinical assessment, but it does help focus the differential by showing whether the pattern fits a normal anion gap, high anion gap, or low anion gap picture.
Stepwise: How to Operate the Calculator
Working with anion gap calculator is straightforward if you know which laboratory values to enter. The goal is to enter the right calculator inputs from the patient’s lab report and let the tool handle the calculations. Below is a helpful step-by-step guide.
Step 1: Find the serum sodium. Look for serum sodium on the lab report. This is the primary measured cation used in the formula. Make sure you use the exact value from the same blood draw as the other electrolytes.
Step 2: Locate the serum chloride. Then, locate serum chloride. Chloride is one of the key measured anions and is essential for the calculation. If you see a high chloride result, that may affect the final interpretation.
Step 3: Identify the serum bicarbonate. Identify serum bicarbonate, sometimes labeled CO2 or total CO2 on the lab report. Because bicarbonate is part of the formula, low bicarbonate often signals a potential acid problem and may support suspicion of metabolic acidosis.
Step 4: Put in the values into the calculator. Enter the three values exactly as reported. Careful calculator inputs matter because even a small entry mistake can lead to an incorrect result. If the calculator asks whether to use potassium, check whether your clinical setting includes it in the formula; many basic calculators do not.
Step 5: Examine the result. The calculator will display the anion gap value. Compare it with the stated reference range or the institution’s lab reference values. The number alone is useful, but it becomes much more meaningful when considered alongside the patient’s acid-base pattern.
Step 6: Evaluate the pattern. Decide whether the result suggests a normal anion gap, high anion gap, or low anion gap. This final clinical interpretation step connects the math to the physiology and helps guide next questions and testing.
Advice: Always select results from the identical serum chemistry test panel. Mixing numbers from separate moments can bias the result and produce a misleading picture of the patient’s condition.
How exactly the Equation Works
The anion gap calculation is based on the connection between measured positive ions and measured charged particles. As commonly written, it is calculated as:
Anion gap = Sodium - (Chloride + Bicarbonate)
It works because sodium is the dominant measured cation, while chloride and bicarbonate are the key measured anion components. The result estimates the space left by other ions that are not directly included in the routine lab panel.
The idea behind the formula is not that something is literally missing, but that the body contains other charged particles that are not measured routinely. These can include acids or other compounds that influence the anion concentration. When those unmeasured anions increase, the gap often increases.
The final number should always be interpreted alongside the appropriate reference range. Different laboratories may use somewhat different ranges depending on assay methods and whether potassium is included. That is why the calculator should be interpreted with the same lab’s values in mind rather than as a fixed absolute.
Interpreting the Result
Once you have the calculated value, the next step is interpretation of the result. The main categories are normal gap, elevated anion gap, and reduced anion gap. Each can suggest a different type of acid-base abnormality or other metabolic issue.
Within-range anion gap: A result within the reference range usually suggests that the balance between measured cations and anions is intact. However, a normal value does not rule out illness. Some forms of metabolic disturbance can still exist with a normal gap, especially if the bicarbonate is low and chloride is compensating.
High anion gap: A increased anion gap often indicates excess acid in the blood or accumulation of extra anions. This pattern is classically associated with acidic metabolic state. It is a strong prompt to look for an underlying cause, such as acid buildup or impaired clearance.
Low anion gap: A low anion gap is less common, but it can occur with low albumin, lab-related issues, or other shifts in measured electrolytes. It is important not to ignore it, because it can reveal a hidden problem or a technical issue in the sample.
In practical clinical reading, the anion gap is best used as part of a broader picture. Consider the bicarbonate level, the chloride level, the patient’s symptoms, and any other relevant findings on the blood test panel.
Accounting for Albumin
Albumin strongly affects the anion gap because it is a negatively charged protein in the blood. When albumin is low, the measured anion gap may look lower than expected. This is why albumin correction is often needed for proper interpretation.
Hypoalbuminemia can obscure a true acid problem. In other words, a patient may have a substantial acid load, but the uncorrected anion gap may appear only slightly abnormal or even normal. Using an adjusted anion gap helps account for that effect.
The corrected or adjusted anion gap estimates what the value would be if albumin were normal. Different calculators may use slightly different correction methods, but the core principle is the same: lower albumin lowers the NAGMA causes apparent gap, so the result should be raised when albumin is reduced.
When using a calculator, check whether it includes an albumin correction field. If it does, enter the measured albumin to get a corrected anion gap. This is especially important in ill patients, where low albumin is common and can alter the interpretation of the lab pattern.
Frequent Causes of an Altered Anion Gap
An altered anion gap often suggests a certain category of illness, though it is not diagnostic by itself. The most common causes are associated with too much acid production, reduced acid removal, or changes in measured proteins and electrolytes.
Increased anion gap causes frequently include:
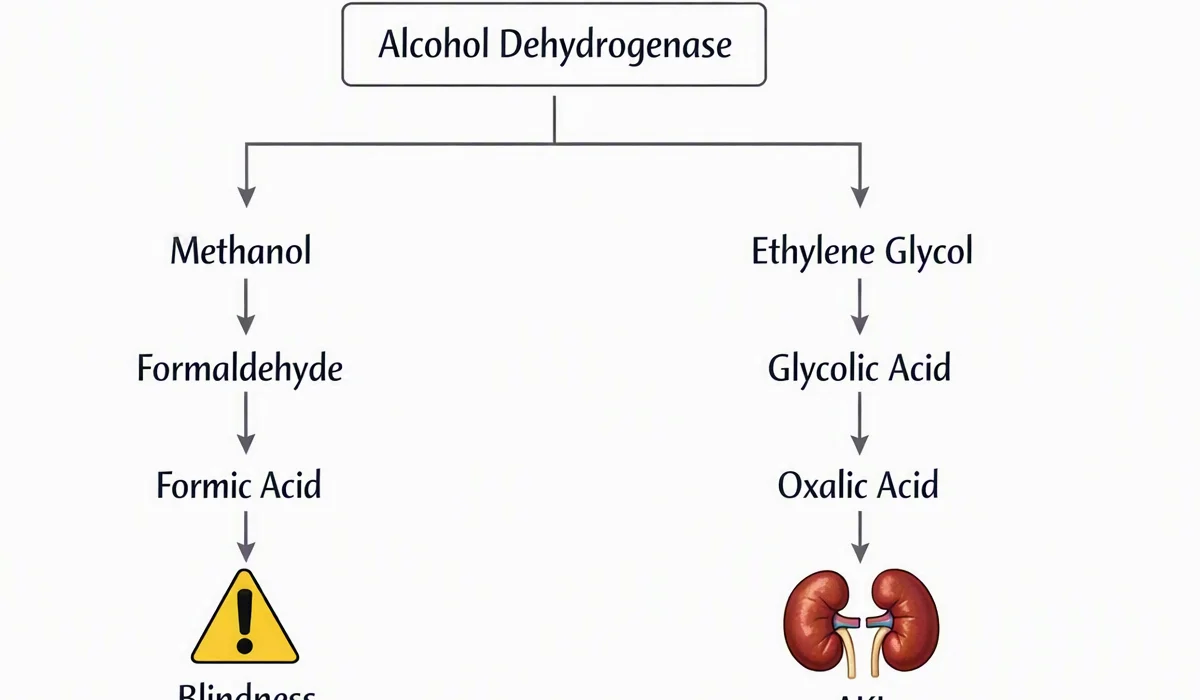
- Lactic acidosis, where lactic acid rises due to poor oxygen delivery, shock, or severe illness Ketoacidosis, which can occur in diabetes, starvation, or alcohol-related states Renal failure, where the kidneys cannot clear acids effectively Toxins, including certain ingestions that generate or contain acid-forming substances
These conditions elevate the burden of acids or unmeasured anions, leading to a high anion gap. In many cases, the gap rises alongside a low bicarbonate, which is another sign that the body is counteracting excess acid.
Reduced anion gap causes are uncommon but may include hypoalbuminemia, some forms of lab interference, or marked alterations in measured ions. If the gap is unexpectedly low, review the sample and the overall clinical context before drawing conclusions.
Because several different disorders can produce similar numbers, the anion gap should be treated as a diagnostic clue, not a final answer. It helps direct the workup, but it does not identify the exact diagnosis on its own.
Common Mistakes When Using the Calculator
Even a reliable calculator can create misleading results if the inputs or interpretation are wrong. The most frequent mistakes are easy to avoid once you know what to watch for.
Lab error: If the specimen was mishandled or the values do not fit the clinical picture, a lab error should be considered. Rechecking the sample or repeating the panel may be necessary before acting on the result.
Unit mismatch: A unit mismatch can cause big problems. Make sure the calculator expects normal AG reference by lab the same units reported by the lab. Entering values in the wrong format can distort the math and lead to a false interpretation.
Missing values: An anion gap depends on complete data. If the report is missing serum sodium, serum chloride, or serum bicarbonate, the calculation will be unreliable. Skip assumptions; use a complete electrolyte panel.
Interpretation error: A numeric result is only part of the story. A normal anion gap does not always mean “normal,” and a high anion gap should be interpreted in context. The most common interpretation error is treating the number as a diagnosis instead of a clue.
Also remember that albumin changes can alter the apparent value. If albumin is low, failing to use albumin correction may hide a meaningful abnormality. For the best accuracy, always review the full blood chemistry panel and confirm the values before making decisions.
FAQ: Anion Gap Calculator Questions
What numbers do I need to use an anion gap calculator?
You usually need serum sodium, serum chloride, and serum bicarbonate. Some calculators also allow albumin so they can provide an adjusted anion gap. Ensure the numbers come from the same blood chemistry panel for accurate clinical use.
What is a normal anion gap?
A normal normal anion gap is within the calculator’s stated reference range. The exact range may vary by laboratory and method, so always rely on the value that matches the lab report. A normal result can still need further assessment if other findings point to an acid-base problem.
Why do you correct the anion gap for albumin?
You factor in for albumin because low albumin can leave the gap appear smaller than it really is. In hypoalbuminemia, the uncorrected value may overlook an important problem. Albumin correction helps show the true adjusted anion gap and improves interpretation.
What does a high anion gap mean?
A high anion gap often indicates excess acid or increased unmeasured anions. Common causes include lactic acidosis, ketoacidosis, renal failure, and certain toxins. It is an important clue in assessing metabolic acidosis and other forms of acid-base disorder.
Can an anion gap calculator diagnose a condition by itself?
No. An anion gap calculator helps with clinical interpretation, but it cannot identify a condition on its own. It is one piece of evidence used to interpret lab results alongside symptoms, exam findings, and other tests. The calculator is most useful when combined with full clinical assessment and lab context.