What the anion gap shows
The anion gap is a useful way to think about acid-base balance using routine electrolytes from a blood test. It compares the major measured cations and anions, especially sodium, chloride, and bicarbonate. In plain terms, the result helps indicate whether there are additional unmeasured anions or other shifts in the body’s chemistry that point toward a particular acid-base disorder.
Clinicians often use the anion gap as a screening tool, not a final diagnosis. A high value can point to metabolic acidosis from causes such as lactic acidosis or ketoacidosis, but the number alone does not show the full story. Likewise, a normal value does not always mean the blood chemistry is normal. The key is clinical interpretation, which requires looking at the full electrolyte panel, the patient’s symptoms, and the broader diagnostic reasoning process.
Another important point is that the calculation reflects the relationship between measured ions and the body’s unmeasured cations and anions. Because the result is indirect, small shifts in serum electrolytes can shift the apparent gap. That makes the anion gap valuable, but also easy to misread if you treat it as a standalone number instead of a clue in a larger differential diagnosis.
How to use an Anion Gap Calculator accurately
An Anion Gap Calculator is especially useful when it is applied with the same attention you would use for any other lab-based decision tool. The calculator typically depends on a serum chemistry panel and may factor in potassium or exclude it depending on the method. Since the formula can vary, the first step is to know exactly which inputs the calculator expects and whether it matches the approach used by your lab.
Before entering numbers, confirm the values for sodium, chloride, and bicarbonate. If the calculator includes potassium, understand that this can slightly affect the result and may influence comparison with a lab-reported reference value. The point is not just to produce an anion gap calculation, but to generate a result that fits the relevant normal range and the patient’s laboratory results.
If applied appropriately, the calculator helps identify a high anion gap pattern, supports recognition of metabolic derangement, and guides next steps in clinical interpretation. When handled poorly, it can create false reassurance or false alarm. A good habit is to review the calculator result with the full blood chemistry, including the patient’s history, medications, and concurrent acid-base data.
Mistake 1: Not correcting for albumin
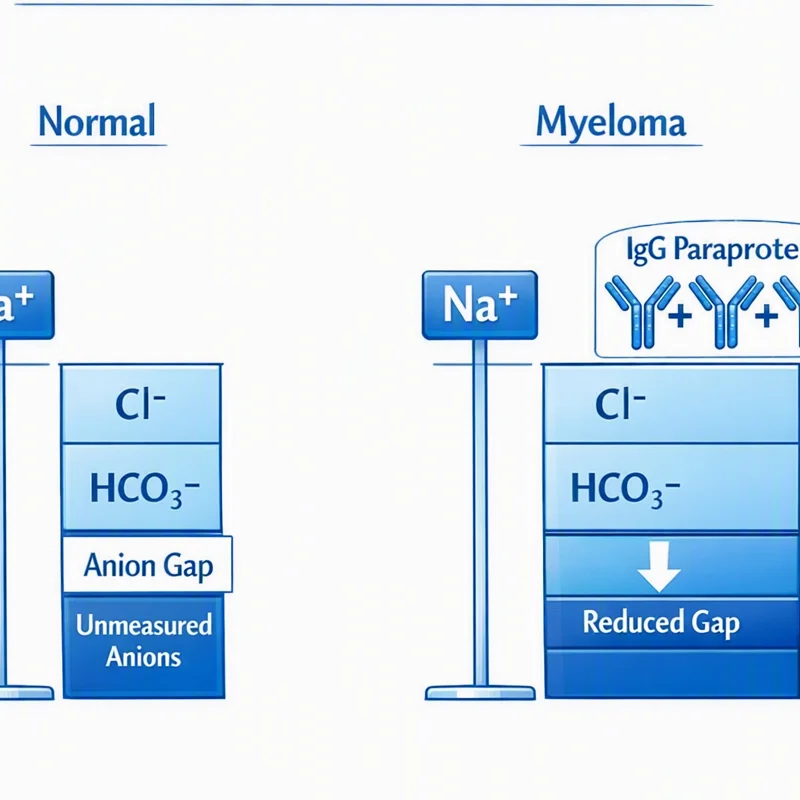
One frequent interpretation errors is not remembering that albumin is a significant contributor to the anion gap. When hypoalbuminemia is identified, the measured gap may look deceptively normal even when there is a true acid-base problem. This happens because albumin functions as an important unmeasured anion, so low levels lower the baseline gap.
This is why albumin correction matters. A corrected anion gap or albumin-adjusted gap can uncover hidden metabolic abnormalities that a raw number misses. If the albumin is low, the apparent normal result should not close the evaluation. Instead, it should prompt you to ask whether the corrected value suggests a metabolic acidosis or other disturbance.
Another important point is that albumin-related changes can be mistaken for a comforting result when total protein is not considered. Total protein does not replace albumin correction, but it can provide context about the patient’s broader nutritional, hepatic, or inflammatory state. The main lesson is that a “normal” anion gap in the setting of hypoalbuminemia is not always truly normal.
Pitfall 2: Overlooking between-labs variation
Not all lab provides the same reference range for the anion gap. Variations in assay method, sample handling, and instrument calibration can alter the result. This is why laboratory variation crucial: a number that looks abnormal in one system may be acceptable in another.
A frequent source of variation comes from the ion-selective electrode used to measure chloride and other electrolytes. As the gap is derived from measured components, a small analytic difference can affect the final calculation. This means you should compare the result with the specific lab’s stated range rather than rely on a generic cutoff memorized from a textbook.
That same issue also affects follow-up testing. If you are monitoring results over time, ensure the same lab or the same methodology is being used whenever possible. If not, you may mistake laboratory variation for a true change in the patient’s metabolic state. Good interpretation depends on understanding that the anion gap is partly a function of the platform, not just the patient.
Trap 3: Missing mixed acid-base disorders
Another major error is thinking that one abnormal number tells the whole answer. Patients can have combined acid-base disorders, where several mechanisms is happening at once. For instance, a patient may have metabolic acidosis from lactic acid buildup and simultaneously have breathing-related alkalosis from sepsis, pain, or anxiety.
Here is where the delta gap and delta-delta calculations become important. They help compare the rise in the anion gap with the fall in bicarbonate. If the changes do not match as expected, there may be an additional acid-base process hidden underneath the obvious one. That kind of mismatch can reveal a mixed disorder that would otherwise be undetected.
For instance, a patient with a high anion gap from lactate-related acidosis may also have a concurrent metabolic alkalosis from vomiting. Or a patient with diabetic acidosis may have an additional respiratory abnormality. The lesson is to avoid using the anion gap as a binary marker. Rather, use it as part of a broader diagnostic thought process strategy that accounts for overlapping processes.
Error 4: Missing normal-gap acidosis
Not necessarily every important acidosis produces a high reading. A patient may have normal anion gap acidosis, also called hyperchloremic acidosis, where bicarbonate decreases but chloride goes up to maintain electroneutrality. In this context, the anion gap may persist within the expected interval even though the patient still has a real acid-base problem.
Typical causes include diarrhea, which leads to bicarbonate loss from the gastrointestinal tract, and renal tubular acidosis, where the kidneys are unable to acidify urine appropriately. These conditions are often ignored when clinicians focus only on high-gap disorders. That can delay treatment and lead to a false sense that the metabolic profile is not concerning.
The practical takeaway is simple: a normal value does not rule out acid-base pathology. If symptoms, history, or the electrolyte pattern suggest a problem, keep assessing. Looking at chloride trends, bicarbonate level, and the overall metabolic panel can help separate hyperchloremic acidosis from other disturbances.
Trap 5: Missing unmeasured cations and toxins
The anion gap can also be altered by unusual substances in the blood. Certain unmeasured cations, such as lithium, can lower or obscure the gap by altering the balance of charged particles. In other cases, toxins create a high anion gap because they form acid or interfere with normal metabolism.
Toxic alcohols are a classic issue. They can lead to severe metabolic derangement and may show up with an elevated gap before the diagnosis is obvious from history alone. Salicylates are another important ingestion because they can create complex acid-base findings, sometimes with an early respiratory component and later metabolic acidosis. This is why toxicologic causes should stay on the differential when the gap and clinical picture do not correlate neatly.
Do not assume that all high-gap states are due only to lactate or ketones. When the numbers do not fit, review the medication list, ingestion history, and mental status carefully. Recognizing unmeasured cations and toxins early can be life-saving and prevents dependence in a single lab-based explanation.
How to interpret this result in clinical context
The anion gap result should always be read alongside the full picture, not in isolation. This means reviewing the arterial blood gas, the patient’s symptoms, vital signs, medication exposure, and the full clinical context. A number that looks important on paper may be expected for that patient’s condition, while a subtle abnormality may be the first sign of a serious problem.
In practice, it helps to ask what the body is trying to tell you. Is there evidence of lactate elevation from poor perfusion, infection, or hypoxia? Are there ketones from insulin deficiency, starvation, or alcohol-related illness? Does the blood gas confirm a primary acid-base disturbance, or is compensation making the picture more complex?
Sound interpretation uses the anion gap as one piece of a broader assessment. The calculator can quickly flag patterns, but the final answer depends on patient-specific data and the direction of the clinical interpretation. If the result does not fit the story, recheck the sample, review the calculation, and revisit the differential diagnosis.
Typical questions about anion gap interpretation
Interpreting the anion gap well requires more than memorizing a formula. It involves understanding acid-base balance, recognizing when a metabolic panel is incomplete, and knowing when to widen the diagnostic approach. The sections below address the most common questions clinicians and students ask when using an Anion Gap Calculator.
What is the most common mistake when interpreting the anion gap?
The most common mistake is treating the number as definitive without considering albumin, the lab’s method, and the broader clinical picture. A raw anion gap can be misleading when hypoalbuminemia is present or when there is significant laboratory variation. Another frequent error is failing to recognize that a normal value does not rule out disease, especially in normal anion gap acidosis.
Why do low albumin alter the anion gap?
Albumin is a key unmeasured anion. When albumin is low, the baseline gap falls, which can hide an elevated gap from another process. For this reason albumin correction is essential. Without it, a patient with a real metabolic problem may appear to have a typical result even when the corrected number is out of range.
Can a normal anion gap indicate a serious acid-base disorder?
Yes, it can. A normal Browse this site value can occur in hyperchloremic acidosis, renal tubular acidosis, or diarrhea-related bicarbonate loss. All of these are meaningful disorders even though the gap is not elevated. A normal result should lead you to assess chloride, bicarbonate, symptoms, and the entire electrolyte panel.
In what way do mixed acid-base disorders affect anion gap interpretation?
Mixed acid-base disorders can make the lab pattern seem inconsistent. For example, a patient may have a high-gap process such as lactic acidosis or ketoacidosis plus a separate process like respiratory alkalosis. The delta gap and delta-delta help determine whether the bicarbonate change matches the gap change, which can reveal a hidden second disorder.
When should toxins or unmeasured cations be considered?
Include them whenever the pattern does not fit common causes or the clinical story suggests exposure. Lithium can change the calculation through unmeasured cations, while toxic alcohols and salicylates can cause dangerous metabolic disturbances. If the anion gap is unexplained, especially in an acutely ill patient, toxin exposure should be kept on the differential diagnosis.